The question that couldn't be ignored
Science is uncomfortable with «it works, but we don't know why.» That discomfort is productive: it drives the kind of relentless inquiry that turns empirical observation into genuine understanding. By the late 1990s, the evidence that PDRN accelerated healing was strong enough to be clinically credible, but the mechanism — the cellular language by which these DNA fragments were communicating with human tissue — remained elusive.
The central puzzle was deceptively simple. DNA's primary job in any cell is to serve as a blueprint: a master set of instructions for building proteins. But PDRN fragments were too small to carry complete genetic instructions. So what exactly were they doing? How were fragments of DNA triggering such profound and consistent healing responses in human tissue?
The hypothesis that made the most intuitive sense — that PDRN was simply donating raw nucleotide material for cells to rebuild their own damaged DNA — was partially correct, but it turned out to be only half the story.
The landmark discovery: a receptor, a lock, and a key
In 1999, a team of researchers published a study that would reshape the understanding of PDRN entirely. Scientists exposed primary cultures of human skin fibroblasts — the cells deep in the dermis responsible for producing structural proteins and maintaining skin's structural integrity — to PDRN. The results confirmed what clinicians had been observing: fibroblast growth rate increased. Cells multiplied. Healing activity accelerated.
The researchers added a critical experimental twist: they introduced a chemical called DMPX, a selective blocker of the adenosine A2A receptor. When DMPX was present, PDRN's proliferative effects disappeared almost entirely. Then they tested the opposite — a chemical that mimics A2A receptor activation, without any PDRN at all. The fibroblasts responded almost identically to how they responded to PDRN itself.
The conclusion was elegant and definitive: PDRN was functioning as a pro-drug — a biological precursor that the body converts into active compounds which then bind specifically to the adenosine A2A receptor. The receptor was the lock. Adenosine, released when PDRN was enzymatically broken down by the body, was the key. And the healing effects were the door swinging open.
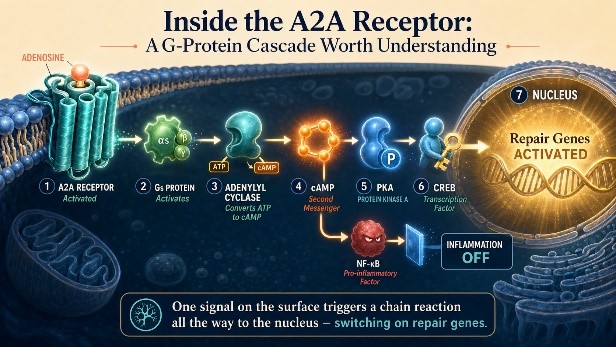
Inside the A2A receptor: a G-protein cascade worth understanding
The A2A receptor belongs to a class called G protein-coupled receptors (GPCRs), the largest family of cell-surface signalling proteins in the human genome. When adenosine binds to the A2A receptor, it triggers a conformational change that activates a G protein inside the cell membrane. This activated G protein stimulates an enzyme called adenylyl cyclase, which converts ATP into cyclic AMP (cAMP).
From there, cAMP activates Protein Kinase A (PKA), which phosphorylates a transcription factor called CREB. When CREB is phosphorylated, it moves to the nucleus and activates gene promoters — switching on a portfolio of regenerative, anti-inflammatory, and pro-angiogenic genes. A single binding event at the cell surface triggers a cascade that reaches all the way into the cell's nucleus.
Importantly, the A2A receptor pathway also suppresses NF-κB — the so-called «master switch» of inflammation. Since NF-κB is the transcription factor responsible for producing pro-inflammatory cytokines such as TNF-α, IL-6, and IL-8, blocking it simultaneously reduces tissue-damaging inflammation while promoting regeneration. This dual property is what makes PDRN so clinically versatile.
The second mechanism: feeding the cellular recycling plant
The A2A receptor pathway wasn't the complete story. A second mechanism, working in parallel, added an extraordinary dimension to PDRN's biology: the nucleotide salvage pathway. When extracellular enzymes break PDRN down in tissue, they produce the full complement of deoxyribonucleosides — the four building blocks of DNA itself. These are absorbed by surrounding cells and fed directly into the salvage pathway, phosphorylated into the active currency DNA polymerases use during replication.
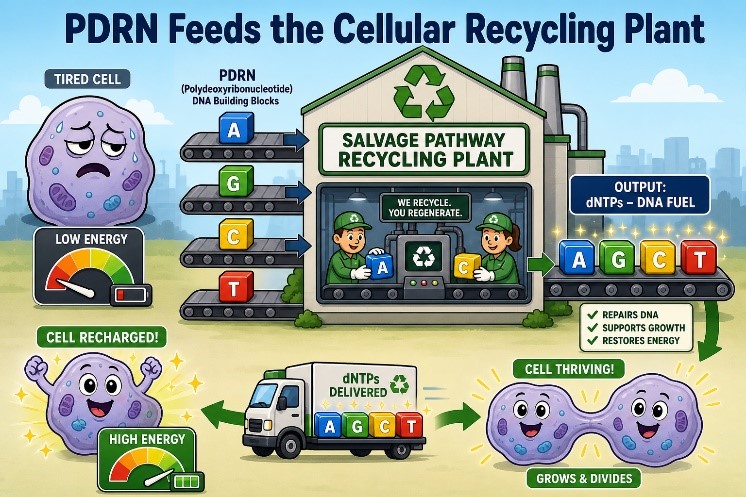
Normally, cells synthesise fresh nucleotides through a complex, energetically expensive process. In tissue that is wounded, chronically stressed, hypoxic, or aged, that energy budget is compromised, and de novo synthesis slows. The salvage pathway offers an energetically cheap alternative: recycle existing nucleosides instead of building new ones from scratch. PDRN floods this pathway with substrate, in the natural ratios present in any DNA.
This creates a uniquely powerful dual action that no simple receptor agonist can replicate: PDRN simultaneously signals cells to regenerate through the A2A receptor cascade, and supplies the molecular fuel those cells need to actually complete DNA replication and divide. It delivers both the instruction and the raw materials.
Why wounds fail, and how PDRN fixes it
The most compelling early validation of PDRN's dual mechanism came from diabetic wound models. Diabetic wounds exhibit critically depressed levels of Vascular Endothelial Growth Factor (VEGF), the master regulator of new blood vessel formation. Without adequate VEGF, capillaries cannot form, oxygen cannot reach the wound, and cells cannot regenerate.
In 2008, Galeano and colleagues published a landmark study in Wound Repair and Regeneration testing PDRN in a genetically diabetic mouse model: PDRN-treated animals showed a statistically significant increase in VEGF by day six, and wound-breaking strength at day twelve was substantially improved. Critically, all of these effects were abolished when DMPX was co-administered — confirmatory proof that VEGF upregulation was happening specifically through the A2A receptor pathway.
A landmark 2014 randomised, double-blind, placebo-controlled clinical trial enrolled 216 diabetic patients with chronic foot ulcers. After eight weeks, complete healing was achieved in only 18.9% of placebo patients, compared to 37.3% in the PDRN group — nearly double. The median time to complete wound healing was 30 days with PDRN versus 49 days with placebo.
The ERK pathway: smarter than a simple switch
A 2023 study in Molecular Medicine Reports investigated how PDRN affects the ERK pathway in two different cell types: fibroblasts and keratinocytes. The results were fascinatingly context-dependent. In fibroblasts, PDRN increased ERK phosphorylation, driving upregulation of type I and type III structural protein synthesis while suppressing matrix metalloproteinases (MMPs) — the enzymes that degrade those structural proteins in aged or damaged skin. When researchers blocked ERK with an inhibitor, PDRN's structural-protein-boosting effects disappeared.
In keratinocytes, PDRN did the opposite — it inhibited ERK phosphorylation, suppressing pro-inflammatory cytokine production. The same molecule, acting on two adjacent cell types in the skin, was doing fundamentally different things, but both were exactly what the skin needed: more structural protein output from fibroblasts, and less inflammatory noise from keratinocytes.
The ischemia insight: flipping the switch from distress to recovery
Research on ischemic skin flaps — where tissue temporarily loses blood supply — showed PDRN dramatically restored blood flow and promoted complete re-epithelialization, measurable as early as day five. PDRN both increased VEGF expression and reduced expression of HIF-1α, the «hypoxia-inducible factor» that accumulates when tissue is oxygen-deprived — effectively switching ischemic tissue from a distress state to a recovery state.
Why this science matters for skin
The gap between hospital wound care and everyday skincare might seem vast, but mechanistically it is a small step. The cellular events that drive diabetic wound healing and the cellular events that drive aesthetic skin regeneration are mediated by the same pathways: fibroblast proliferation, structural protein synthesis, MMP suppression, VEGF-driven microvascular support, and NF-κB-mediated inflammation control.
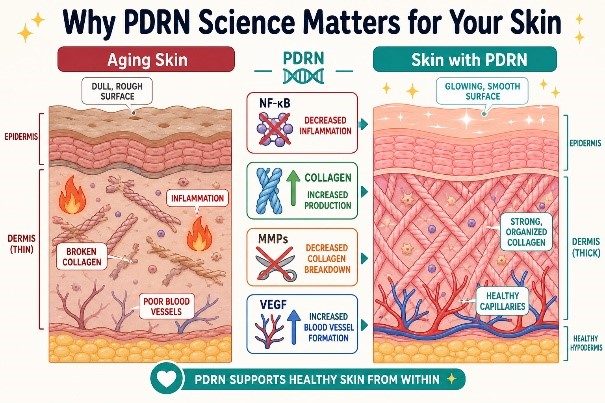
Skin aging is, in cellular terms, a slow convergence of the conditions that create chronic wounds: chronically elevated inflammatory cytokines, depleted structural proteins from chronically elevated MMPs, reduced fibroblast activity, impaired microcirculation, and DNA damage from UV radiation that outpaces the salvage pathway's ability to repair it. When Korean dermatologists began using PDRN as an aesthetic injectable in the 2010s, they were applying two decades of mechanistic science — knowing exactly which cellular pathways they were activating, and why.
…The science wasn't borrowed from beauty. The beauty was born from the science…
What makes PDRN unique among A2A agonists
PDRN is not the only adenosine A2A receptor agonist in medicine — regadenoson, approved by the FDA as a cardiac stress agent, is another. But PDRN's dual mechanism, signalling and substrate, means it occupies a category of its own. Pure receptor agonists can activate the healing signal but cannot supply the nucleotide building materials cells need to complete DNA replication; simple nucleotide supplementation cannot supply the receptor-level activation signal. PDRN does both.
According to the 2017 comprehensive review by Squadrito and colleagues in Frontiers in Pharmacology, this dual action is directly linked to PDRN's specific DNA origin, molecular weight range (50–1,500 kDa), and manufacturing process. Not all PDRN products are equivalent — biological activity depends on having the right chain lengths, the right purity, and the right production method.
The foundation is set
By the early 2010s, the scientific community had a clear, multi-layered picture of how PDRN worked at the molecular level: a pro-drug that generated A2A receptor agonists, triggering a cascade that switched on regenerative gene expression and suppressed inflammatory signalling, while simultaneously feeding the nucleotide salvage pathway with metabolically economical building blocks. This was not a molecule of mysteries anymore — it was a molecule of mechanisms, well-characterised, clinically validated, and ready to transform aesthetic medicine.
Key scientific references
Thellung, S., et al. (1999). Involvement of A2 purinergic receptor subtypes in the trophic activity of PDRN on human skin fibroblasts. Life Sciences.
Squadrito, F., et al. (2017). Pharmacological Activity and Clinical Use of PDRN. Frontiers in Pharmacology, 8:224.
Galeano, M., et al. (2008). Polydeoxyribonucleotide stimulates angiogenesis and wound healing in a diabetic mouse model. Wound Repair and Regeneration, 16(2), 208–215.
Altavilla, D., et al. (2014). The effect of PDRN, an adenosine receptor A2A agonist, on the healing of chronic diabetic foot ulcers. Journal of Clinical Endocrinology & Metabolism, 99(5), E746–E753.
Kim, J.H., et al. (2023). Polydeoxyribonucleotide exerts opposing effects on ERK activity in human skin keratinocytes and fibroblasts. Molecular Medicine Reports, 28(3), 166.
Galeano, M., et al. (2012). Polydeoxyribonucleotide restores blood flow in an experimental model of ischemic skin flaps. Journal of Vascular Surgery, 55(2), 479–488.
Fredholm, B.B., et al. (2008). The A2A adenosine receptor: a GPCR with unique features? British Journal of Pharmacology, 153(S1), S310–S321.



